Fair question, and you should ask it. Socket preservation is not automatic. It matters most when you intend to replace the tooth, when the tooth is in the smile zone where ridge collapse shows, or when the remaining bone walls are already thin. It matters less for some back teeth where nothing will be placed and the neighbors are stable. Ask your dentist to show you the 3D scan and say specifically what they are protecting against. If the answer is vague, push back.
Bone Grafting and Socket Preservation in Vestal, NY
Almost nobody arrives at this page because they wanted a bone graft. You are here because a tooth has to come out and someone mentioned preserving the socket, or because you asked about an implant and were told there is not enough bone to hold one. Both conversations tend to arrive out of nowhere, and both sound like an upsell until somebody explains the biology.
So here it is. The bone in your jaw that surrounds a tooth is called the alveolar ridge, and it exists for exactly one reason: to hold that tooth. Your body is efficient. Take the tooth away and it stops maintaining the bone that was supporting it, and begins reclaiming the material for use elsewhere. That process starts within days of an extraction and moves fastest in the first months.
It happens in two directions. Width goes first, as the walls of the empty socket collapse inward without a root between them. Height follows, and it goes faster in people wearing a denture or a partial, because the pressure from the appliance accelerates it.
The best time to protect the bone is the day the tooth comes out.
Socket preservation adds a few minutes to an extraction you were already having. Rebuilding a ridge that collapsed three years ago is a separate surgery, a longer heal and a considerably larger bill.
Socket Preservation: The Step That Happens at the Extraction
When a tooth is removed with preservation in mind, the extraction itself is done differently. The goal is to lift the tooth out while leaving the thin walls of bone around it intact, rather than levering against them. That alone changes how much ridge you keep.
The empty socket is then filled with a grafting material that behaves like a scaffold, and covered with a membrane or plug that dissolves on its own. Over the following months your own bone grows into that scaffold and gradually replaces it. What you end up with is your bone, in roughly the shape and volume it had when the tooth was there, ready for whatever comes next. Our Learning Center walks through how grafting prepares a site for an implant step by step.
That last part matters even if an implant is years away or not in the plan at all. A ridge that has kept its shape supports a bridge or a denture better, holds the gum line and the facial contour in place, and leaves every option open. A ridge that collapsed closes options permanently.
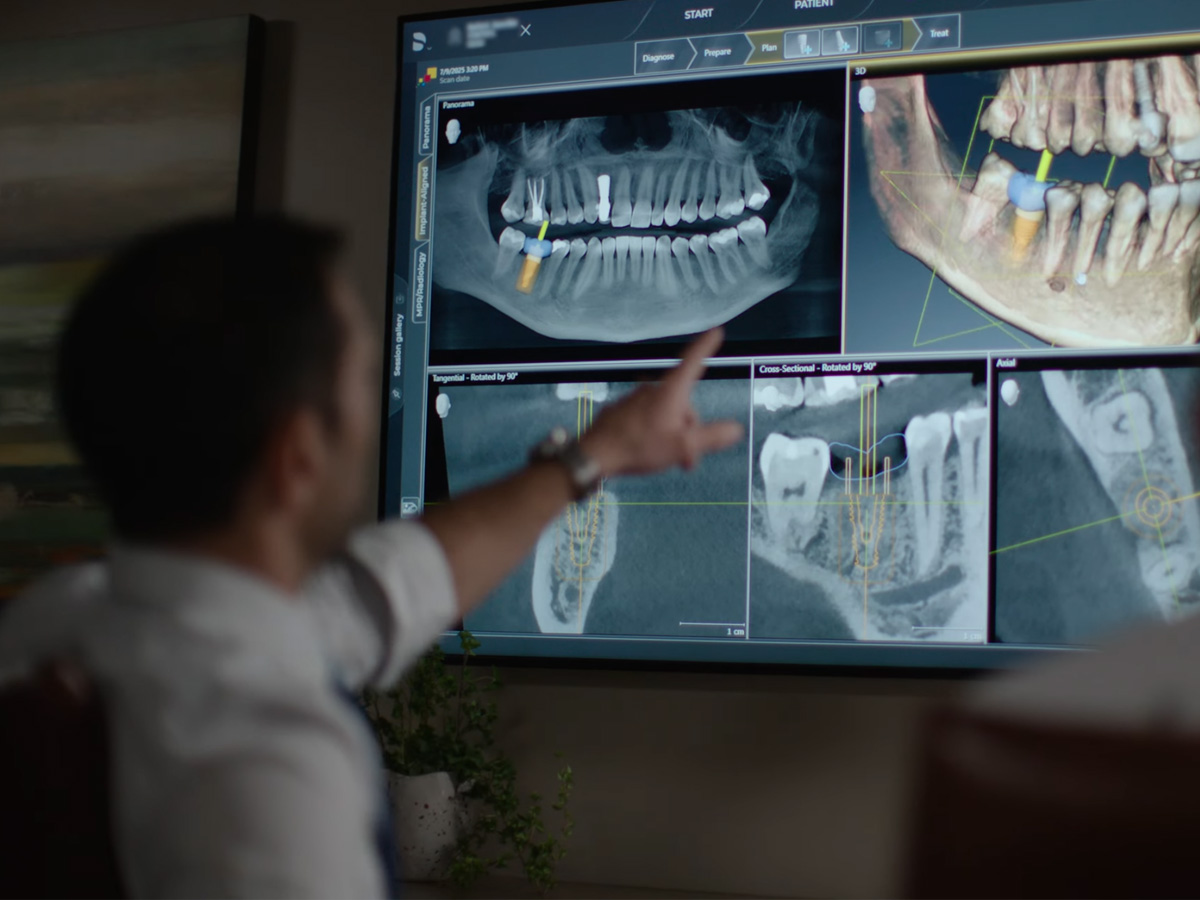
Whether you have enough bone is a question of millimeters, and a flat x-ray cannot answer it.
Our Orthophos SL 3D imaging shows the ridge in three dimensions at a lower radiation dose than conventional cone beam systems, so your dentist can measure actual bone width and height and see exactly where the nerve and sinus sit before planning anything. See our knowledge and technology in full.
When the Bone Is Already Gone
Plenty of patients come to us years after an extraction, or after long term gum disease quietly dissolved the bone around teeth that are still in place. That situation is treatable, it just takes a different procedure.
- Ridge augmentation rebuilds width or height on a ridge that has already flattened, so an implant has something to anchor into.
- Sinus lift addresses upper back teeth, where the sinus cavity tends to expand downward into the space a molar root used to occupy. The sinus floor is raised and the space beneath it grafted.
- Immediate placement is sometimes possible, where the extraction, the graft and the implant happen in one appointment. It depends entirely on how much healthy bone is left and whether there is active infection. Your 3D scan answers that, not a guess.
For cases where healing needs support, we use a platelet-rich plasma centrifuge. A small sample of your own blood is spun to concentrate the platelets and growth factors it already contains, and that concentrate is placed at the surgical site. It is an adjunct rather than a substitute for good surgical technique, and your dentist will tell you whether it is worth using in your particular case rather than applying it to everything.
Today I had an extraction of a cracked molar (to install an implant later) as the result of a popcorn kernal... Of course I was a little anxious, but they made me feel at ease. They use the latest methods and my comfort was important to them. I am amazed by their skill everytime.
Jack O. · Google Review
Where the Graft Material Actually Comes From
Most practices skip this question. Patients ask it constantly, usually after the appointment, so here is the straight answer. There are four sources, and all four are routine:
- Your own bone, taken from elsewhere in your jaw. Excellent biologically, but it means a second surgical site.
- Processed human donor bone, screened and sterilized through the same tissue bank system used across medicine and surgery. This is the most common choice for socket preservation. No living cells remain, so there is no rejection risk in the way people imagine.
- Bovine derived mineral, processed down to the mineral scaffold. It holds its shape well over time, which is useful where volume has to be maintained.
- Synthetic materials, manufactured to mimic bone mineral, with no biological source at all.
Your dentist will tell you which one they are recommending and why. If you have a preference on any grounds, including religious or personal ones, say so. There is almost always a workable alternative, and it is a much easier conversation before the appointment than after it.
Why Patients Across Greater Binghamton Trust Us With This
Bone grafting is the part of implant dentistry where preparation shows up years later. It is worth asking who is doing yours.
- Training specific to this work. Dr. Nolan Robinson is a Misch Implant Institute graduate and a member of the International Congress of Oral Implantologists, and studied dental implants and bone physiology during his training in Buffalo. Dr. Troy Robinson and Dr. Levi Upham both focus on dentoalveolar surgery, which is extractions, implant placement and bone augmentation. Read about the team.
- Planning before cutting. Orthophos SL 3D imaging and computer guided treatment planning let our dentists run the surgery virtually before you are in the chair.
- One practice, start to finish. The extraction, the graft, the implant and the final crown all happen here, with the same people. Nothing gets handed between offices with a story that changes along the way.
- Here since 1955. Four generations of Southern Tier families have been treated in this practice.
- Comfort handled properly. Sedation, advanced sedation monitoring and A-dec 500 chairs for longer appointments.
Questions We Hear About Bone Grafting
-
Do I actually need this, or is it an add-on?
-
How bad is the recovery?For socket preservation done at the time of an extraction, recovery is essentially the recovery from the extraction itself. Expect soreness and swelling for a few days and follow the aftercare instructions carefully, particularly around not disturbing the site. Larger procedures such as a ridge augmentation or a sinus lift involve more swelling and a longer settling period. Our Learning Center covers what implant surgery actually feels like, and the honest answer for most people is less than they braced for.
-
How long until I can have the implant placed?Typically several months, because the graft has to be replaced by your own bone before it can support an implant. The exact window depends on the size of the site, the material used and how you heal, and your dentist will confirm it with a follow up scan rather than a calendar. Waiting considerably longer than recommended is not harmless either, since a grafted ridge with nothing loading it slowly resorbs again. There is a window, and we will tell you when you are in it.
-
I lost a tooth years ago. Is it too late?Almost certainly not. You have missed the easy window, which means grafting is now a procedure of its own rather than a few extra minutes during an extraction, but ridge augmentation and sinus lifts exist precisely for this. The first step is a 3D scan to measure what is actually there. Plenty of patients who were told elsewhere that they were not implant candidates turn out to be, once the bone is rebuilt. The Learning Center covers what determines implant eligibility.
-
What if I do not want an implant at all?Preserving the socket still usually pays off. A ridge that holds its shape supports a bridge or a partial denture far better, keeps the gum line even so the gap is less visible, and helps maintain the facial contour that bone loss in the jaw slowly changes. It also leaves the door open if you change your mind in five years, which a collapsed ridge does not. That said, it is your decision, and if you are certain, say so and we will plan accordingly.
-
Will insurance cover bone grafting?Coverage varies more here than almost anywhere else in dentistry. Some plans cover grafting when it is tied to a covered extraction, some treat it as part of implant coverage, and some exclude it. Medical insurance occasionally applies for larger reconstructive cases. We will work out your specific benefits and give you a written estimate before you agree to anything. Our payment options page lists the plans we work with and the financing available.
If a tooth is coming out, let's plan ahead.
Preserving the socket at the time of extraction keeps your options open and makes any future replacement simpler and more predictable. A short consultation and a 3D scan is all it takes to plan it properly.
Request an Appointment
Proudly Serving Patients in the Following Communities
- Apalachin NY
- Bainbridge NY
- Binghamton NY
- Castle Creek NY
- Chenango Forks NY
- Choconut PA
- Conklin NY
- Coventry NY
- Endicott NY
- Endwell NY
- Greene NY
- Harpursville NY
- Johnson City NY
- Kirkwood NY
- Little Meadows PA
- Maine NY
- McDonough NY
- Norwich NY
- Owego NY
- Oxford NY
- Port Crane NY
- Port Dickinson NY
- Triangle NY
- Vestal NY
- Windsor NY
